
Newsletter articles

Catch up on highlights from our newsletter, featuring stories, resources, and upcoming opportunities to engage.
Learn about local and national events where you can connect, raise awareness, and support the lung cancer community.
Explore real stories honoring survivors and those remembered through their lasting legacy. Select a category to find stories that resonate most with you.
Find practical advice, emotional support, and resources to help you or your loved one cope with the challenges of living with lung cancer.
Stay informed about the policies that impact the lung cancer community and ways you can get involved.
Explore breakthroughs and ongoing studies in lung cancer research, from clinical trials to cutting-edge therapies and prevention.
Catch up on highlights from our newsletter, featuring stories, resources, and upcoming opportunities to engage.
Explore news and updates shaping the lung cancer landscape—from scientific breakthroughs and organizational milestones to awareness campaigns and community highlights.

September 18, 2026
Download this blog to print or share with someone impacted by non-small cell lung cancer.
What is stereotactic body radiation therapy?
Stereotactic body radiation therapy (SBRT) is a special type of cancer treatment that uses many small beams of high-dose radiation. The beams enter the tumor at different angles and overlap to deliver a high dose of precise radiation. SBRT is also sometimes called stereotactic ablative body radiotherapy (SABR).
How is SBRT different from traditional radiation?
Traditional radiation therapy exposes a slightly broader area of healthy tissue around the tumor to radiation as compared to SBRT. It’s often delivered in small daily doses, over several weeks, allowing healthy tissue near the tumor to recover between treatments.
SBRT can be completed in a shorter time period than traditional radiation therapy. Because it delivers a higher dose of radiation that is precisely aimed at the tumor, nearby healthy tissue is less affected, resulting in fewer side effects.
Both traditional and SBRT radiation therapy may be used in non-small cell lung cancer (NSCLC).
When is SBRT used and why?
SBRT is a commonly used lung cancer treatment for both early and late-stage NSCLC.
In early-stage NSCLC, SBRT may be used along with surgery, or it may be used alone in cases where surgery is not recommended due to other medical conditions or risk factors.
In later stages of NSCLC, SBRT may be used along with other treatment types to treat a small number of metastases (cancer that has spread from the lung to other parts of the body) or to treat a tumor that has come back after prior treatment.
What are the possible side effects of SBRT?
SBRT is generally well tolerated, and most people receiving SBRT do not experience severe side effects. However, like all cancer treatments, SBRT can cause some side effects, depending on the size and location of the tumor, as well as your overall health.
Possible short-term side effects (during treatment or within the first few weeks after) include:
- Skin changes, such as dry skin or reddening
- Fatigue
- Mild cough or shortness of breath
- Mild chest discomfort
- Nausea
Possible long-term side effects (months to years after treatment) include:
- Radiation pneumonitis (Inflammation of the lung tissue near the treated site)
- Lung fibrosis (scarring) of the treated area
- Chest wall pain
Most short- and long-term side effects resolve on their own without specific treatment, while others may be managed with support from your healthcare team.
Ask your healthcare team how to prevent or manage these effects and when to seek emergency care.
Questions about SBRT for your healthcare team
- Is SBRT the best option for my specific diagnosis?
- How many treatment sessions will I need?
- Are there activities I should avoid during or after treatment?
- What side effects should I be aware of, and how should I manage them?
- Will I need other treatments, such as surgery or chemotherapy?
- How often will I need follow-up scans after treatment?
If you want to learn more about SBRT or have questions about lung cancer, please contact our free HelpLine at 1-800-298-2436 or email support@go2.org

September 16, 2026

Bringing people together, raising awareness, and creating hope for those impacted by lung cancer are what keep Daniel Craig, MS, TTS, and the team at Tammy Walker Cancer Center coming back to Shine a Light on Lung Cancer® year after year. Since 2017, the center has partnered with the North Central Regional Coalition and Masonic Cancer Alliance to host an event where survivors and families can connect, loved ones are remembered, and the community can learn more about lung cancer.
For Craig, cancer program manager and cancer outreach coordinator at Tammy Walker Cancer Center, Shine a Light has become an important annual tradition and an opportunity to start conversations that continue well beyond the event itself.
Bringing people together around lung cancer
Shine a Light on Lung Cancer is the largest coordinated lung cancer awareness program in the world. Every November during Lung Cancer Awareness Month, healthcare facilities, community organizations, businesses, patients, caregivers, and loved ones come together through events designed to educate, connect, and celebrate the lung cancer community.
At Tammy Walker Cancer Center, those connections are at the heart of the event.
Craig says Shine a Light helps create community connections, raise awareness, inspire hope, and keep lung cancer at the forefront of conversations throughout the year.
And sometimes, the most meaningful connections happen when people have the opportunity to hear directly from someone who understands what they are going through.
Craig says some of the most powerful moments at past Shine a Light events have come from pairing a local healthcare professional with a cancer survivor. Medical information and statistics can help people better understand lung cancer, but hearing a survivor share their personal experience can bring that information to life.
Together, those perspectives can create what Craig describes as a sense of hope and inspiration.
Turning awareness into conversations that matter
Shine a Light events can also help people learn about lung cancer risk, screening, early detection, and resources available in their own communities.
For Craig and his community, one topic in particular, radon, has generated conversations.
Radon is an environmental risk factor for lung cancer, but it had not previously been a major focus for the North Central Regional Coalition. When Shine a Light events included information about local radon levels, Craig noticed that community members wanted to know more.
That response helped the coalition recognize an opportunity for additional education.
It’s an example of what can happen when lung cancer awareness becomes a community conversation. People can ask questions, discover information they may not have encountered before, and learn about resources that can help them take action for themselves or someone they love.
There’s no single way to Shine a Light
One of the strengths of Shine a Light is that every community can make the event its own.
Events can be in person, virtual, or hybrid. Some feature patients and survivors sharing their stories. Others include remarks from healthcare professionals, educational information or giveaways, opportunities to remember loved ones, or activities that bring the community together.
An event doesn’t have to be large or elaborate to make a difference.
Craig encourages organizations interested in hosting their own event to start small and build from there. Over time, an event can grow as more patients, families, volunteers, healthcare professionals, and community partners become involved.
At Tammy Walker Cancer Center, collaborating with local organizations and connecting Shine a Light with existing community events has helped build relationships and reach more people.
But no matter what an event looks like, the purpose remains the same. The event aims to ensure that people affected by lung cancer have an opportunity to connect, learn, remember, and find hope.
A light that keeps shining
After years of hosting Shine a Light, Craig says the event has come to represent something deeply meaningful for the Tammy Walker Cancer Center team.
It means celebrating local survivors, remembering loved ones lost to lung cancer, helping people learn about prevention, screening, and early detection, and bringing a community together to raise awareness for lung cancer.
Those moments of connection extend far beyond a single event in November. Each conversation, story shared, question asked, and new connection can help build greater awareness and a stronger lung cancer community all year long.
Ready to shine a light? Learn more about Shine a Light on Lung Cancer and how you can get involved in bringing awareness, connection, and hope to the lung cancer community. Have questions? Contact Katie Morello at shine@go2.org.
September 16, 2026

Before lung cancer, Mayya was used to having a plan for everything. As a high performing marketing executive in the video game industry, she managed multimillion-dollar campaigns, led large teams, and was interviewing for a major new leadership role when her life took an unexpected turn. At home, she and her husband were raising 2 young children and juggling the beautiful chaos that comes with life as a busy young family.
By all accounts, things were going well.
“I was essentially corporate Barbie,” Mayya said.
She was healthy, active, and the last person anyone would have expected to be diagnosed with lung cancer. But looking back, Mayya knew something wasn’t right.
Trusting herself

It started during her second pregnancy. Mayya wasn’t gaining weight the way she had during her first pregnancy. She constantly felt like she had to remind herself to eat and found herself raising concerns with her care team at appointment after appointment.
After her daughter was born, other symptoms followed. She was exhausted, but she had a newborn and a toddler. Of course she was exhausted. She lost the baby weight quickly, but everyone congratulated her for it.
Then came the cough. At first, that was easy to explain away too. Her family had endured the endless parade of illnesses familiar to many families with children in day care. But when everyone else recovered, Mayya didn’t. Her cough lingered, as did the fatigue and the general feeling that something was off.
When she sought medical care, her concerns were dismissed, and she was told it was likely allergies or a lingering infection. In fact, the first doctor barely listened to her, looking at the clock before she ever looked at Mayya. When Mayya asked for an X-ray, the doctor said she didn't need one. "It doesn't sound dry," the doctor said. "I haven't coughed yet," Mayya replied.
She walked to her car in the parking lot and called the office back immediately to make a new appointment with a different doctor. Then that appointment got canceled, so she drove straight to urgent care where she found a doctor who was finally willing to dig a little deeper.
An X-ray showed some cloudiness. It was not a clear answer, but it was something. Mayya was given antibiotics for possible pneumonia and sent home, but she didn't get better.
"I was feeling slightly worse every day," she remembered.
Then came Mother's Day. Mayya was sitting on the floor playing with her kids, exhausted, when she heard a sudden, clear, and urgent voice in her head: “If you don't go to urgent care right now, you're going to die.”
"It had to be my grandmother," she said. "She had a flair for the dramatics."
She turned to her husband. "I know it's Mother's Day, but I have to go."
At urgent care, the same doctor who had seen her earlier that week sent Mayya directly to the ER, worried she had a dangerous blood clot in her lungs known as a pulmonary embolism. Before going to the ER, she went home, breastfed the baby, left a stash of milk in the fridge, and said goodbye to her 3-year-old son, who asked how she'd get home.
"You guys will pick me up in a little bit," she told him.
At the ER, a CT scan brought unexpected news. There was no blood clot, but there was a mass in her chest.
"I knew in that moment it was cancer," Mayya says. "I knew."
The long road to a name
For weeks, the working assumption was lymphoma. Nobody brought up lung cancer because she was young, had no known risk factors, and her blood work was perfect.
She was admitted to the hospital where she had a bronchoscopy and got sent home. The interventional pulmonologist who did the procedure told her, “My job is to get you answers." The bronchoscopy came back inconclusive, but he was honest that something didn’t look right.
Then came a PET scan. Every lymph node from her neck to abdomen as well as her bones lit up. Still, the results pointed to lymphoma because her lung itself was barely glowing.
Following that, Mayya was matched with an oncologist at Duke Cancer Center. The coordinator on the phone mentioned access to clinical trials. “Trials?” Mayya thought. “I don't need trials for something as vanilla as lymphoma.”
She looked the doctor up. He was a thoracic oncologist. Her stomach dropped. She wondered whether perhaps he was moonlighting in hematology.
Mayya was at the beach with her family when she opened her test results. They reported stage 4 (IV), ALK-positive, non-small cell lung cancer (NSCLC). “Metastatic, metastatic, metastatic,” the word repeated down the page. No clean margins.
"That's how I found out," she said. "At the beach house, by myself, piecing it together."
A zebra in a world full of horses
There is a concept in medicine called Occam's Razor which states that when you hear hoofbeats, you should assume horses, not zebras. In other words, doctors are taught to look for the most likely explanation before considering something more rare. Mayya knows this, and she understands it. "But I am a zebra," she said. "And doctors are so used to looking for horses that when a zebra is standing right in front of them, they try to make it a horse."
At 38 years old, Mayya became part of a growing group of people who are reshaping what the world thinks lung cancer looks like. Young, healthy, active, and with no traditional risk factors, these people do not appear to doctors as “typical” lung cancer patients and often experience long delays in diagnosis because of it.
In other words, they are zebras.
A zebra among zebras
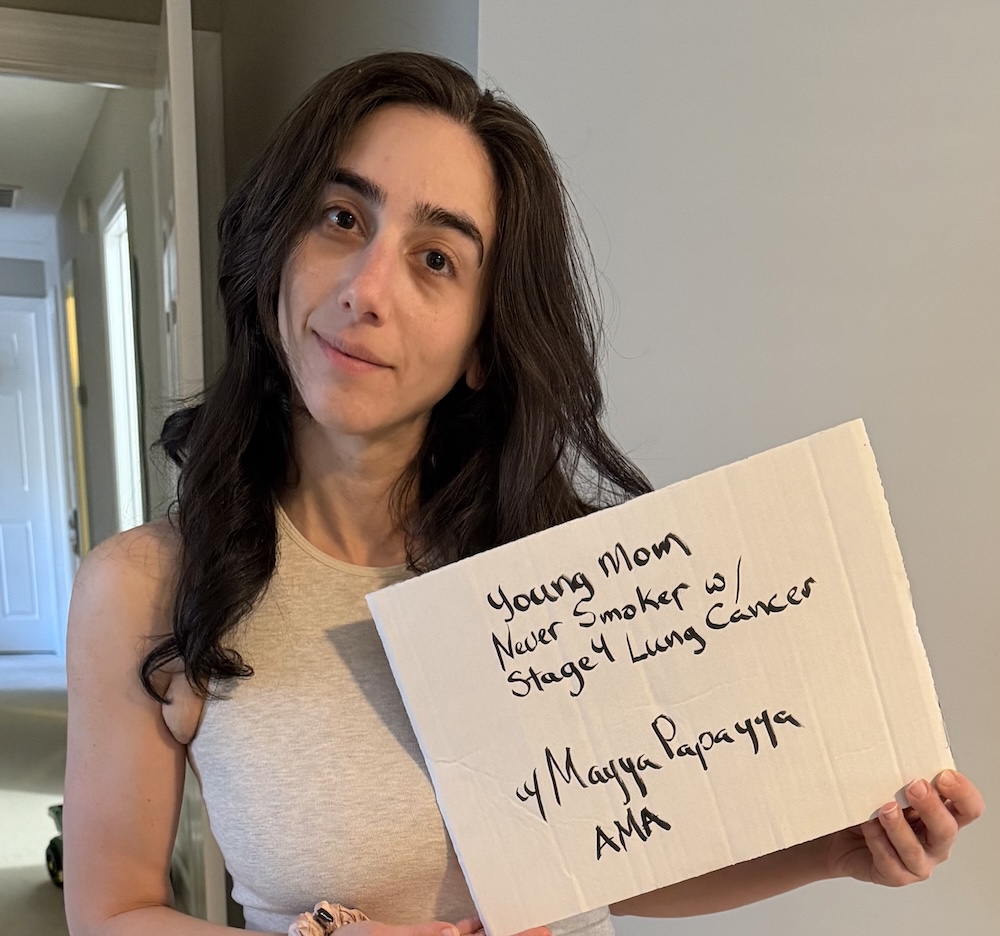
If being diagnosed with lung cancer at 38 made Mayya a zebra, her experience after diagnosis only reinforced the point.
She started Lobrena (lorlatinib), a targeted therapy for ALK-positive lung cancer. Her response was extraordinary. By her first scan, nearly all evidence of disease in her bones and lymph nodes had disappeared. Her doctor had never seen anything like it.
She was told that she was lucky to have this genetic type, and she and her care team hoped she would be one of the large number of ALK-positive patients having many years of progression-free survival on the drug.
However, 8 months later, the cancer progressed. And once again, Mayya found herself outside the expected path.
"I call myself the ghost of Christmas future, walking around rattling chains in ALK communities," she said with a laugh. "They say the median survival on lorlatinib is 7 years. I made it 8 months. I represent a possibility that nobody wants to think about."
Being someone whose cancer progresses quickly on a treatment that works for most others carries its own weight. Mayya has talked to others in the same position and found something unexpected: shame.
"There's almost an embarrassment in it," she said. "You see those graphs showing how well people do, but then you fall off at the 2% mark. Nobody likes to talk about those people. Unfortunately, a third of people on the drug will have an experience like mine. We have to understand our experiences too.”
Mayya is now on a combination regimen of chemotherapy, lorlatinib at a reduced dose, and Avastin (bevacizumab), a plan developed in collaboration between her primary oncologist at Duke and a second-opinion team at Dana-Farber Cancer Institute, including 1 of the leading ALK researchers in the country.
"Between the 2 of them, they came up with a plan that I don't think either would have come up with on their own," she said. “They’re a great team.”
Who gets your best 8 hours?
Life changed for Mayya in large and small ways after her diagnosis. Despite being a successful professional and her family’s bread winner, she made the decision to step back from work and go on disability. It wasn't a defeat. It was a choice.
"Statistically speaking, the best I was going to feel was right after diagnosis," she said. "My doctors aren't trying to cure me; they are managing a downhill slide. And I realized that I was giving the best 8 hours of my day during the best part of my life to my CEO. I had to ask myself, who did I actually want to be giving those hours to?"
The answer was her kids, her husband, and her mom, who now lives with them. Her family, whom she had always prioritized, became her full focus. They plan trips, go to swim lessons and ballet recitals, and squeeze adventures into the windows between her every-3-week infusions on the days when she feels well enough to go.
Her biggest fear is not her own death. It is the crater she would leave behind. She worries for her children, who were 3 years old and 8 months old when she was diagnosed; her mother, who has already buried a husband and her own mother, and whose only child is now fighting lung cancer; and her husband, who she used to joke better get his own health together so that he would live a long life with her and their kids.
“I feel like I’m the bomb that went off in my family,” she said. “Cancer didn’t go off as a bomb in our house. I went off.”
For Mayya, the hardest part of a metastatic diagnosis has never been thinking about herself. It has been thinking about the people she loves most and the grief they might carry.
The stakes are different
Living with metastatic lung cancer means learning to live with uncertainty.
"My body is a haunted house," Mayya said. "It's like a Halloween haunted house where there's a bunch of creaks and jump scares. Some of them are real and some of them are not."
A blurry eye might just be eye goop. A sore hip might be because you slept wrong. Or it might be something more. The challenge is that there is no way to know immediately, and every new symptom carries a question mark.
Mayya also thinks about the people who don't speak up as readily as she does. The short responders who disappear from online communities because they feel like they've let everyone down, the patients whose doctors dismiss them, the women who hear "you're probably fine" when something is clearly not right. She wants them to know they are not alone.
"The stakes are different for patients than they are for doctors," she said. "If a doctor misses something, they've had a bad day, but you're not coming home to your children."
Her advice is to think about your medical team the way you'd think about a contractor working on your house. You would never do your own electrical work. You trust their expertise and value their training, but you still ask questions, get second opinions, and stay actively involved. In this case, your doctor is the expert, but you’re still the one who lives in the house, so you get to have an active say in what’s happening to it.
Planning anyway

Today, Mayya continues to advocate, raise her children, spend time with her friends and family, and push for more research. She speaks openly about uncertainty, progression, and the experiences that don't always fit neatly into the success stories people want to hear. Because that's part of being a zebra, too. You don't always fit the expected narrative, but you keep moving forward anyway.
She thinks often about the people in her community who are living with ALK-positive lung cancer as something closer to a chronic disease, surviving for a decade or more, and weathering setbacks along the way but still here.
"Those are my heroes," she said. "People who can stumble forward for a decade are my spirit animals. I'll take it. I'm happy just stumbling down the road for another 20 years."
It may not be the path she expected, but she's still moving forward 1 scan, 1 infusion, 1 family trip, and 1 ordinary day at a time.
A lung cancer diagnosis can bring a lot of questions, emotions, and uncertainty. GO2 for Lung Cancer's free HelpLine connects you with trained specialists who can provide support, answer questions, and help you find resources along the way. Whether you're newly diagnosed, in treatment, or navigating survivorship, you don't have to face it alone.
Call us at 1-800-298-2436 or email support@go2.org to learn more.

August 5, 2026

Felipe had spent his entire life focused on how the body works and how to keep it working well. With a background in exercise physiology and injury prevention, his career was built around helping people recover, rebuild, and, whenever possible, avoid injury altogether. So, when something didn’t feel right in his own body, it stood out immediately.
In 2019, Felipe was running a half marathon with 2 clients when he noticed a cough that felt different from anything he had experienced before.
“I couldn’t catch my breath, which was very unlike me,” he said. “People were actually stopping and asking if I was okay.”
He finished the race, but the symptoms stayed. He was diagnosed with chronic bronchitis and asthma and prescribed inhalers and steroids, but things didn’t improve.
By 2021, after months of worsening symptoms and delays in care during the COVID-19 pandemic, Felipe went to urgent care. His oxygen levels were dropping to dangerous levels, and he was sent to the emergency room where a CT scan revealed nodules in his lungs.
Soon after, he was diagnosed with lung cancer. “It was so completely unexpected,” he said. “I was healthy in every way, and I’d never smoked, so getting lung cancer wasn’t something I even thought was possible.”
“I lost my identity”
At the same time, other parts of Felipe’s life were shifting just as dramatically. A flood destroyed his 10,000-square-foot gym overnight, and he was about to turn 65, a big milestone that included a long-time dream of relocating to Florida.
In April 2021, Felipe underwent a lobectomy. The procedure was successful. Physically, he recovered quickly. But what followed was something he hadn’t anticipated.
In the months following surgery, Felipe expected to return to the life he once knew. Instead, he felt himself drifting further and further away from it. For someone whose life had always been grounded in discipline and driven by purpose, the shift was deeply unsettling.
“I lost my identity,” he said. “I lost my purpose.”
At first, it didn’t have a name; it just showed up in patterns he couldn’t ignore. Overeating, drinking more than he should, not training, constantly consuming news and social media, yet he was still showing up for work, still meeting responsibilities. From the outside, everything looked intact. But inside, something felt off and disconnected.
“I was just not myself at all,” he shared. “I was in a really dark place.”
Then he came across a description of those behaviors being called “slow suicide.” That stopped him in his tracks. Not because suicide had ever crossed his mind, it hadn’t, but because he recognized the pattern. It was a slow drift, quiet neglect, and disconnection from himself.
That realization pushed him to try to understand what he was actually experiencing. Through research he realized it had a name: high-functioning depression.

A turning point
Felipe doesn’t identify a single moment that changed everything, but rather a more gradual realization that he needed to do something different.
His approach was to return to training, nutrition, and structure, the fundamentals that had served him well throughout his life. He sought out accountability and rebuilt his routines with intention.
Over time, the changes were significant.
“I got into the best shape of my life,” he said, “and I dragged myself out of a dark place while doing it.”
But more importantly, he began to see his experience differently and as an opportunity to return to the life of serving people that had once defined him.
Rethinking “survival”
As people around him began using the word “survivor,” Felipe found himself pushing back against it. To him, it didn’t go far enough.
“Just surviving cancer is a very low bar,” he said.
Felipe believes that for people with early-stage cancer, surviving is not the only endpoint. It can be a beginning. What matters more is how you rebuild, how you take care of yourself, and how you move forward.
A disconnect
As Felipe moved further from treatment, he noticed something that surprised him and inspired his next steps.
“There’s a disconnect between the end of medical care and the re-starting of real life,” he said. “Your appointments become less frequent and the structures that guide you through your diagnosis and treatments fade away.”
What to expect when your care ends isn’t always clearly defined, and for Felipe, that gap seemed like an opportunity to help others navigate what had proven tricky for him.
From experience to action

Felipe hadn’t planned to write a book about his experiences, but as he reflected on what he had gone through, he realized that much of what had helped him to navigate life after cancer wasn’t easy to find in one place.
“There are resources out there,” he said. “But they’re not organized. You have to go find a little bit here, a little bit there, and piece it together yourself.”
What he wanted to create was something different. Not a memoir, and not a set of rigid instructions, but a starting point. A way for people to begin making sense of what comes next.
That idea became his book, “Don’t Call Me a Survivor: Thriving Beyond Cancer.”His book brings together the core elements of training, nutrition, mindset, and accountability, all of which helped him rebuild. It introduces the idea that these things don’t work in isolation.
“Everything has to work in the same direction,” he said. “It’s the synergy of it all coming together that creates big change.”
At its core, the book is about awareness. Helping people recognize that the period after treatment can be just as challenging as the diagnosis itself, and that without structure or support, it’s easy to drift.
From there, the book points toward something more: a path forward. Building something different. After writing the book, Felipe began building something more structured, something that could help others not only understand what they were experiencing but begin to move forward too.
At his gym in South Florida and through his virtual client roster, his approach reflects what he learned through his own experience; that progress doesn’t come from one thing alone.
His “Phoenix Path” model moves from awareness to action, with a 90-day program that offers daily structure, weekly support, and a focus on rebuilding from the ground up.
It’s not about doing everything at once, he emphasizes. It’s about starting where you are.
That might mean starting with health before fitness and building a foundation through nutrition, breathing, and basic movement before pushing further. It might mean rebuilding confidence, rediscovering a sense of purpose, or creating structure where it’s been lost. And it always means meeting people where they are.
“Everything can be improved,” he said, “I help people focus on the fundamentals to feel better in a comprehensive way that’s unique to them, what they’ve been through, and where they want to go.”
Full circle
Earlier this year, Felipe heard from one of the runners from that half marathon where his symptoms first appeared. Now approaching 80, that same runner, Dan, was preparing to complete another half marathon, this time after his own cancer diagnosis.
On May 17, 2026 Felipe joined Dan for that race.
The moment felt full circle in a way he couldn’t have imagined years ago, when he was struggling to understand what was happening in his own body. To run alongside this man again after everything they’ve both been through seemed almost surreal.
For Felipe, this kind of real, human, and hard-earned connection is what it’s all about.
Looking ahead
Today, Felipe continues to train, build, and connect, drawing directly from his experience with lung cancer. He’s also focused on reaching more people, especially those navigating the uncertain space between treatment and whatever comes next.
He still undergoes regular scans, and there is still uncertainty. But his relationship with that uncertainty has changed. Instead of waiting for answers, he focuses on what he can control: how he trains, how he eats, and how he shows up each day.
For Felipe, surviving was never meant to be the end of the story. It was the beginning of a different experience, one rooted not just in getting through, but in moving forward with intention.
Because for him, the real question isn’t whether you survive. It’s what you do next.
A lung cancer diagnosis can bring a lot of questions, emotions, and uncertainty. GO2 for Lung Cancer's free HelpLine connects you with trained specialists who can provide support, answer questions, and help you find resources along the way. Whether you're newly diagnosed, in treatment, or navigating survivorship, you don't have to face it alone.
Call us at 1-800-298-2436 or email support@go2.org to learn more.

August 5, 2026
Some insurance plans use a policy called step therapy, sometimes known as fail first. This means some plans may require you to try a lower-cost cancer therapy before they will cover the therapy your healthcare team originally recommended.
Step therapy is not new, but it is getting renewed attention because of recent changes to Medicare Part D could lead some Medicare prescription drug plans to rely more on tools like prior authorization (getting approval before a treatment is covered), formularies (the list of medications a plan covers), and step therapy. Health plans can use step therapy tools to help control costs by encouraging the use of less expensive or preferred medications before covering more expensive treatments.
The good news is that the step therapy policy does not appear to be widely used for many lung cancer drugs today. GO2 is closely monitoring these policy changes to help protect timely access to appropriate treatment. This is especially important in lung cancer because new therapies continue to be approved by the U.S. Food and Drug Administration (FDA), giving patients more treatment options. Lung cancer treatment is often guided by biomarkers. Biomarker testing results help your healthcare team determine which therapy is most appropriate for you, making timely access to that treatment important.
That is why GO2 supports ongoing legislative and policy efforts such as the Safe Step Act. If enacted, the legislation would help protect patients from unnecessary delays by making it easier to receive a timely exception when step therapy is not medically appropriate.
GO2 recently joined coalition letters, including efforts led by the MAPRx Coalition, expressing concern that recent changes to Medicare Part D payment could lead some Medicare prescription drug plans to rely more on tools like step therapy and prior authorization. These policies could make it harder to get the treatment your healthcare team believes is best for you.
For those interested in learning more, organizations like Aimed Alliance offer resources on step therapy policies, including state laws and patient rights.
GO2 will continue to monitor how these policies are implemented and advocate for approaches that protect timely access to the most appropriate care.
A lung cancer diagnosis can bring a lot of questions, emotions, and uncertainty. GO2 for Lung Cancer's free HelpLine connects you with trained specialists who can provide support, answer questions, and help you find resources along the way. Whether you're newly diagnosed, in treatment, or navigating survivorship, you don't have to face it alone.
Call us at 1-800-298-2436 or email support@go2.org to learn more.

August 5, 2026

When Paul Poblete signed up to run the New York City half marathon, he wasn't just chasing a personal goal. Every training run, every early morning, and every mile had a deeper purpose.
Paul joined the GO2 for Lung Cancer Endurance Team to honor his father, who was diagnosed with combined small cell lung cancer (CSCLC) in 2021, and to help make a difference for other families facing the disease.
What started as marathon training became an opportunity to raise awareness, inspire others, and support the lung cancer community in a meaningful way.
We recently caught up with Paul to learn more about what motivated him to join the GO2 Endurance Team, what he learned along the way, and what advice he has for others considering taking on a race for a cause.
Running for something bigger than yourself
For Paul, choosing GO2 as his charity partner was deeply personal.
"My family was directly impacted when my father was diagnosed with CSCLC in 2021," he shared. "I understand the grief and uncertainty that families experience. I wanted to do something that could help make an impact, not only by raising money but also by raising awareness."
Like so many families, Paul's life changed after his father's diagnosis. Training for a marathon became more than a fitness challenge. It became a way to channel his energy into something positive while honoring his father's experience and supporting others navigating lung cancer.
"I wanted to run for a cause that had impacted not just my family, but so many others around the world."
Finding purpose through the GO2 Endurance Team
Training for a marathon requires commitment, discipline, and countless hours on the road. Paul says knowing that every mile represented something bigger than himself helped keep him motivated.
"Having the ability to raise awareness while raising funds for a personal cause was such a fulfilling feeling," he said.
He also appreciated the support provided through the GO2 Endurance Team.
"The organization provided all the resources I needed to have a successful campaign. From fundraising tips and tricks to a dedicated running coach, everything was there. The entire process was a lot of fun."
For Paul, the combination of training, fundraising, and connecting with a community united by a common purpose made the experience especially meaningful.
"Training and contributing to something bigger than myself really kept me grounded and grateful."
Every donation came with a mile

One of the most creative parts of Paul's fundraising campaign was finding a way to personally thank every donor.
He promised to dedicate 1 mile of training for every $10 donated. During those runs, he would give donors a shoutout on social media. For supporters who weren't on social media, he recorded personalized videos during his training runs and sent them directly.
The idea not only encouraged donations but also kept people engaged throughout his marathon journey.
"I was telling everyone that I would dedicate a mile during training for every $10 they donated," Paul explained. "I'd post a story during that run with their shoutout."
The approach quickly gained momentum.
"I even had friends donate just so they could make me run," he laughed.
By consistently sharing updates, celebrating donors, and inviting others into his journey, Paul kept his campaign visible while making every supporter feel like they were part of the experience.
The power of community
While fundraising was an important goal, Paul says one of the biggest surprises was the overwhelming support he received.
"I was surprised by how many people in my network wanted to support the cause, regardless of how close we were."
Many donations also came with something even more meaningful: personal stories.
"A lot of people shared how cancer had impacted their own lives. The support from everyone was inspiring."
Those conversations reminded Paul that lung cancer affects far more people than many realize. His campaign became an opportunity not only to raise funds, but also to create space for people to share their own experiences and honor loved ones.
Advice for future marathon runners
For anyone thinking about tackling a marathon, Paul's advice is to stay patient and enjoy the process.
"Stay consistent, but remember that progress isn't linear," he said. "There will be times when it gets hard, and you'll want to give up, but in the end it will all be worth it."
He also recommends finding others to train alongside.
"Find friends who want to train with you or join a run club. Running with a group makes it much more enjoyable."
Above all, he encourages runners not to lose sight of the experience itself.
"Have fun and enjoy it. It will be one of the most rewarding experiences of your life."
Advice for future fundraisers
Paul's fundraising success also came from being willing to share his story often and in different ways.
His advice?
"Utilize all your resources to spread awareness, from word of mouth to social media, even LinkedIn. Cast a wide net and repost often."
“People want opportunities to support causes that they care about,” he says. “Sometimes they simply need to be asked.”
Creating a fun, interactive campaign helped people feel personally connected to his fundraising goals and kept the momentum going from start to finish.
Ready to run for hope?
Whether you're an experienced runner chasing your next marathon or someone looking for a new challenge with purpose, the GO2 Endurance Team offers an opportunity to turn every mile into hope for people affected by lung cancer.
As Paul's story shows, fundraising is about much more than reaching a finish line. It's about honoring loved ones, building community, raising awareness, and helping create a future with better outcomes for everyone affected by lung cancer.
Join the GO2 Endurance Team and help us confront lung cancer one mile at a time

August 5, 2026
Leslie lives in St. Augustine, FL with her husband, Ken, and their elderly rescue cat. Her children are grown and live in Maryland and Washington, DC. When not traveling, Leslie can be found soaking up the sunshine at the nearby beach.

When Leslie's cough wouldn't go away, she did what most people would do; she went to her doctor. Then she went back again. And again.
She tried antibiotics and inhalers from her allergist, but nothing helped. Meanwhile, the cough worsened, her breathing became more difficult, and the active lifestyle she loved started slipping away. At the time, Leslie was teaching fitness classes, yet suddenly she found herself struggling to catch her breath.
As the weeks passed, Leslie became increasingly concerned. Her lymph nodes had become noticeably swollen, and she was getting sicker by the day. Although her primary care physician finally ordered a chest CT scan, the appointment was weeks away.
Friends urged her to stop waiting, and finally she listened. She drove herself to a nearby emergency room (ER), expecting to learn she had pneumonia or some other explanation for her symptoms. Instead, a CT scan performed at the hospital revealed a mass in her lung.
“Here’s why you can’t breathe”
The doctor in the ER returned to her room carrying a piece of paper.
"He said, 'I have good news. Your blood work is normal, and your COVID test is negative,’” Leslie remembered. “Then he handed me the scan results and said, 'Here's why you can't breathe.'"
Reading the report herself, Leslie saw the words "lung mass."
"I started screaming, 'Am I going to die?'"
Alone in the hospital room, she called her husband in a panic. Then, something remarkable happened. Her next-door neighbor, an oncologist, happened to be on call that day.
"She walked into my room, and it was like an angel at my bedside," Leslie said.
Her neighbor sat with her, held her hand, and said, “we’ll figure this out together.” Those words became an anchor during one of the most frightening moments of her life.
Finding hope in biomarker testing

A biopsy soon confirmed that Leslie had lung cancer. Because the cancer had already spread to her lymph nodes, doctors knew it was advanced. Like many people diagnosed with stage 4 (IV) lung cancer, Leslie immediately feared the worst.
"All I could think was, 'I'm going to die. Am I going to see my daughters get married? Do I want to be buried or cremated? What’s going to happen to me?' My brain just spiraled."
Her neighbor, however, knew there was another important piece of information still to come: biomarker testing. The wait was agonizing. When a lab error delayed her results for nearly a month, she spent long days sitting outside in the sunshine, reading books, and trying to keep her mind occupied.
When the results finally came through, her neighbor actually printed them out and walked them over to Leslie’s house. She said, "This is good news!"
Leslie's cancer had tested positive for an ALK biomarker, and she heard a phrase that many people with ALK-positive lung cancer have heard before.
"You've won the cancer lottery."
At first, the statement felt impossible to understand.
"It didn't feel like I was winning any lottery," Leslie said.
But as her doctors explained what the ALK biomarker meant, Leslie began to understand. Advances in targeted therapies were allowing many people with ALK-positive lung cancer to live much longer and better than ever before. For the first time since her diagnosis, she felt a glimmer of hope.
The worst club you never wanted to join
Not long after her diagnosis, Leslie discovered the ALK Positive support community, a patient-founded and patient-driven nonprofit organization committed to transforming the future for everyone affected by ALK-positive cancer. No doctor had suggested it. She found it herself. The impact they had on her was profound.
"The ALK Positive group saved my life," she said.
At the time, Leslie was preparing to undergo radiation treatment for brain metastases. She already had the mask made and appointments scheduled. Then, members of the ALK Positive community encouraged her to pause and ask more questions.
"They said, 'Wait. Let the treatment work first.'"
After discussing options with her medical team, Leslie decided to hold off. It turned out to be a good decision. The targeted therapy worked. Her brain metastases responded without radiation.
For Leslie, it was an early lesson in the power of connecting with others who had walked the same path. She found people who had been living with ALK-positive lung cancer for as long as 10 years or more. She found friendships, practical advice, and reassurance that life could eventually feel normal again.
"You won't always be thinking about cancer," people told her. "It gets better."
They were right. Today, Leslie regularly attends ALK Positive events and has formed close friendships within the community.
"Lung cancer is the worst club you never wanted to join," she said, “but we have the best members.”
Learning to accept help
If there was another unexpected gift in the midst of Leslie's diagnosis, it was discovering just how deeply she was loved.
After Leslie’s diagnosis, her people started to show up for her in important and practical ways. Friends delivered meals. Cards arrived in the mail. Flowers showed up at her door. People researched treatment options, shared resources, and offered support in every way they could.
"The kindness was overwhelming," she said.
At first, Leslie found that accepting help felt uncomfortable. Over time, however, she realized that allowing people to help was a gift for them, too.
Looking back, Leslie describes the experience in a way she has never forgotten.
"It's almost like I died and I was at my own funeral," she said. "It was such a gift. I got to see how much people love me while I'm alive."
During the hardest period of her life, she experienced something beautiful.
"I felt like the luckiest person because who gets to experience that? Most people don't get to know how loved they are and how much they’ve meant to people."
Leslie’s friends across the world also helped her raise over $8,000 last year to donate to ALK Positive, which has contributed to the over $10.8 million in patient research funding since 2017. She is beyond grateful for their support of research.

Looking toward the future
Today, Leslie and her husband have retired and moved to Florida, a decision influenced in part by her diagnosis. Rather than waiting for someday, they're embracing the life they had always hoped to build. There are home projects to finish. Trips to plan. New adventures to take. She’s planning for the future in ways she never expected when she was first diagnosed.
Leslie is also participating in a clinical trial that is exploring new ways to prevent resistance to targeted therapies. The experience has deepened her appreciation for the researchers and physicians working to improve outcomes for people living with lung cancer.
"The research gives me so much hope," she said.
Less than 2 years ago, Leslie was wondering if she would live long enough to see her daughters' futures unfold. Today, she's busy planning her own.
June 5, 2026
When we try to characterize small cell lung cancer (SCLC), we typically define it by its stage, either extensive stage or limited stage. We don't often delve further than that; that's about as specific as we'll hear. However, you may be surprised to learn that there are actually 4 unique subtypes of small cell lung cancer, each with its own characteristics. The reason these aren't often discussed, though, is that for a while we weren't certain what this information meant. Yes, there are differences among these 4 types at the cellular level, but what does that really mean for the person living with the disease? In recent years, though, this has begun to change. Scientists have been working to uncover how these small differences can potentially have a great impact on the future of personalized medicine and small cell lung cancer. Here, we'll discuss a little bit about each of these 4 subtypes, and how the treatment landscape may shift to accommodate them in the future.
To differentiate the types of SCLC, we have to look at the different proteins that are inside of the cancer cells. These special proteins can help determine how the genes of the cancer cells express themselves, which in turn can impact how these cells grow, reproduce, and react within the body. By taking a blood sample and looking at the circulating tumor DNA (ctDNA) to examine these factors, doctors and scientists can see what type of subtype a person's SCLC is.
SCLC Subtype-A
These are SCLC type cancers where there is a high expression in the cells of a factor called ASCL1. This is the most common subtype, found in between 40% and 50% of cases. Some early research shows that this subtype might be more susceptible to a type of drug called BL-2 inhibitors. These drugs work by blocking a protein inside of the cells that can then cause the cell to die. Some research suggests that this sub-type, after treatment with chemotherapy, may convert to sub-type I (discussed lower down).
SCLC Subtype-N
This subtype means that a person's SCLC cells have a lot of the factor NEUROD1. This factor is important to helping certain specialized cells grow and function within the body, and it is found in high levels in many cases of extensive-stage disease. This subtype is found in about 20% of SCLC cancers. While this subtype can mean the cancer is a bit faster in how it grows and spreads, it is also more sensitive to treatment with a type of drug called Aura-Kinase inhibitors. These are still in trials for SCLC, and we are monitoring the progress of this research for future uses.
SCLC Subtype-P
Having the subtype of SCLC-P indicates that your cancer has higher levels of the POU2F3 factor. This is a factor used by specialized cells that line the respiratory and digestive systems. In healthy cells, this helps them to recognize foreign bodies and protect against them, but when mutated, it can drive the subtype of SCLC. It's a bit rarer than those described above and is in 12% to 15% of cases. Fortunately, research is beginning to show that this type of SCLC may respond better to a class of experimental drugs called PARP inhibitors. These drugs, though still in trial, have been shown to stop the damaged DNA in cancer cells from replicating, preventing the spread of more cancerous cells.
SCLC Subtype-I
Finally, our last class of SCLC subtypes is SCLC-I. This stands for inflamed SCLC, and indicates that, rather than having higher levels of certain proteins, the cells have a lot of inflammation occurring, and a high level of immune cells within the environment. Because of this, research has shown that this subtype may have a stronger response to immunotherapy agents than other small cell lung cancers. This is a less common class of SCLC, found in about 10-15% of cases.
It is important to know that, when looking at how these sub-types may affect a person's prognosis, there was no difference noted in the length of a person's overall and progression free survival. This means that having one subtype over another doesn't seem to have an impact on how long they will live, or how serious their disease might be. As shown above though, it can impact what treatment types may be more effective, and can help oncologists think about which types of treatment they should try first. It can also useful when a person is considering clinical trials that they may want to join.
If you want to learn more about managing small cell lung cancer and what options are available, please reach out to us. GO2’s HelpLine is a free, one-on-one service that connects patients and caregivers with experienced staff who can provide guidance, resources, and, most importantly, hope!
References:
- Baine MK, Febres-Aldana CA, Chang JC, Jungbluth AA, Sethi S, Antonescu CR, Travis WD, Hsieh MS, Roh MS, Homer RJ, Ladanyi M, Egger JV, Lai WV, Rudin CM, Rekhtman N. POU2F3 in SCLC: Clinicopathologic and Genomic Analysis With a Focus on Its Diagnostic Utility in Neuroendocrine-Low SCLC. J Thorac Oncol. 2022 Sep;17(9):1109-1121. doi: 10.1016/j.jtho.2022.06.004. Epub 2022 Jun 24. PMID: 35760287; PMCID: PMC9427708.
- Dahlstrom, Erin. “Advances in Small Cell Lung Cancer Classification.” MD Anderson Cancer Center, 25 Nov. 2024, www.mdanderson.org/cancerwise/advances-in-small-cell-lung-cancer-classification.h00-159702279.html.
- Schwendenwein A, Megyesfalvi Z, Barany N, Valko Z, Bugyik E, Lang C, Ferencz B, Paku S, Lantos A, Fillinger J, Rezeli M, Marko-Varga G, Bogos K, Galffy G, Renyi-Vamos F, Hoda MA, Klepetko W, Hoetzenecker K, Laszlo V, Dome B. Molecular profiles of small cell lung cancer subtypes: therapeutic implications. Mol Ther Oncolytics. 2021 Feb 6;20:470-483. doi: 10.1016/j.omto.2021.02.004. PMID: 33718595; PMCID: PMC7917449.
- The Asco Post Staff. “Study Identifies Four Unique Subtypes of Small Cell Lung Cancer.” Ascopost.com, 2026, ascopost.com/news/january-2021/study-identifies-four-unique-subtypes-of-small-cell-lung-cancer/. Accessed 30 Apr. 2026.

June 5, 2026
Donna Thompson is a 3-time survivor of early-stage, non-small cell lung cancer, thriving more than a decade since her first diagnosis. After 2 surgeries to remove portions of her right lung, she carries forward an experience that deepens her commitment to lung cancer awareness, mental health advocacy, and building supportive communities. Donna shares her story to inspire hope, reduce stigma, and elevate survivor voices. Her advocacy spans education, outreach, and research collaboration within the lung cancer community. She speaks at wellness and community events, using her experience to empower others navigating illness and recovery. Professionally, Donna is the director of Human Resources and a SHRM Certified HR leader, known for leading with empathy and practical insight, and supporting people through complex workplace challenges. She finds strength - literally and emotionally - through faith, fitness training, and time in nature. For her, movement is medicine, and advocacy is a calling rooted in compassion and resilience.
Donna remembers the exact moment everything changed. It was September 2015, and she went to the emergency room for something else entirely. Her blood sugar was dangerously high, and she wasn’t feeling right. They ran tests, monitored her, and sent her home. The next day, the ER doctor called her and said the radiologist saw a mass in her lung and that she should have it checked out right away.
At 45 years old, and having no smoking history, lung cancer wasn’t on her radar. It wasn’t on anyone else’s either.
“Everyone I talked to was like, ‘You’re too young. You’ve never smoked. This is probably not lung cancer.’”
But within 5 weeks, after scans, a biopsy, and what she still calls “the longest 5 weeks of my life,” Donna had her answer. It was lung cancer after all.
"The best possible situation”
Looking back, Donna sees the moments that led to her lung cancer diagnosis a little differently.
“I always say that was God getting my attention, whispering to me in the quiet, still moments," she said.
The tumor was stage 2 (II) and operable. In many ways, it was the best-case scenario for a diagnosis no one expected. Her surgical team moved quickly.
“She told me, ‘This is the best possible situation. It’s in a good location. We can take it out.’”
By the end of November, just 2 months after that ER visit, Donna had surgery, and for a moment, it felt like the worst might already be behind her.
When the plan changes
Initially, Donna was told she wouldn’t need chemotherapy. The surgery had been successful, her margins were clean, and everything pointed in the right direction.
Then the pathology report came back. It showed that her tumor was more complex than expected. It was an unusual form of adenocarcinoma that didn’t behave in typical ways. Her case was sent to multiple cancer centers, and the recommendation shifted.
“I remember my surgeon calling me herself,” Donna said. “She said, ‘I told you one thing, and now it’s changing, and I need to explain that to you.’”
A second opinion confirmed it: chemotherapy was recommended. Donna agreed, but her body had other plans.
When treatment becomes the crisis
“Every time I got chemo, I ended up in the ER,” she said. “Something was always going wrong.”
After just two treatments, it was clear that this wasn’t sustainable. Her oncologist made the call.
“He said, ‘Your body can’t handle this. We’re done.’”
It was a moment that carried both relief and uncertainty. The treatment meant to protect her was, instead, putting her in danger. And so, once again, Donna adjusted.
“I didn’t survive to be basic.”
In the months that followed, Donna made a decision that would shape everything that came next.
“I didn’t survive to be basic,” she said.
Instead, she poured herself into her health and started working with a trainer, changing her diet, and reclaiming a sense of control over her body.
“I got into the best shape of my life,” she said. “I came off medications. My A1C went back to normal. Everything changed.”
But the transformation wasn’t just physical. It was also about identity.
“The cancer gave me more than it took from me,” she said. “I learned who I am, how strong I can be, and what I really need in the world. I learned what and who are important to me. It put such a clear focus on what I want for my life.”
Finding community and belonging
Still, parts of the experience felt isolating.
“I kept meeting people, and they were all stage 4 (IV),” she said. “I felt like, am I even supposed to be here?”
She was grateful for her outcome, but that gratitude came with a quiet tension.
“I didn’t want to take up space in their groups,” she said. “But I still needed support too.”
And there was something else. “I didn’t see anyone who looked like me.”
It wasn’t until years later, through social media connections, introductions, and small group conversations, that Donna found what she had been missing: a close-knit circle of Black women who truly understood her experience.
“We started meeting regularly, talking, and supporting each other,” she said. “There’s something about being with people who understand you completely without you having to explain that changes everything. They know what they did for me, and what we do for one another. Finally, I had community.”

A second diagnosis, and a different reality
For nearly 7 years, Donna focused on moving forward, rebuilding, and holding onto the belief that she had come through something and grown because of it.
Then, in 2022, everything shifted again. This time, it wasn’t a symptom that sent her back to treatment. It was a scan.
“My scans went from showing nothing to showing a tumor the same size as my first diagnosis,” she said. “I was just so shocked because I wasn’t expecting anything.”
As Donna began to piece together what had happened, the story became even more complicated. The tumor hadn’t appeared overnight. When her new care team reviewed her prior scans, they discovered that the growth had been visible as far back as 2018, but it had been missed.
The radiologist who originally read the scan had not flagged it, and even more concerning, it became clear that her oncologist had never reviewed the images directly.
“That was the moment for me,” Donna said. “I realized no one had really been looking out for me the way they should have. I felt like a number, and I’m a relationship person. This matters to me.”
It was a turning point, not just medically, but emotionally. What initially felt like a sudden recurrence became something harder to process. It was a missed opportunity for earlier intervention.
Another treatment crisis
This time, Donna’s treatment plan included a targeted therapy designed specifically for EGFR-positive lung cancer that would allow her to take a lower dose of chemo, which they hoped she would tolerate better. It felt like progress and a better path.
But after a second surgery, adjuvant chemo, and introducing the new treatment, her body began to struggle again in a different and even more frightening way, this time in response to the targeted therapy.
After multiple attempts to adjust the dosage, the new medicine ultimately led to kidney failure, a serious complication that forced yet another shift in her care and another redefinition of what “moving forward” would look like.
It was also the moment that changed how Donna understood her own story.
“I used to say that cancer gave me more than it took from me,” she said. “And I believed that until my kidneys failed. Recovering from that took nearly all I had. I’m still trying to fully move on from how traumatic that year was.”
“I also have to remind myself how remarkable it was that I overcame this,” she said. “My nephrologist said my recovery was miraculous, and it does feel like a total miracle now.”

Living in the in-between
Today, Donna is once again in a place that many people with lung cancer know all too well: waiting.
In July 2025, after recovering from kidney failure, her care team radiated 2 new spots. They chose radiation because it was the gentlest option for her. Recent scans have shown new nodules that Donna and her care team are just watching, for now.
“They’re watching them and trying to decide what to do next,” she said. “And with my treatment history, not every option feels like a good one.”
It’s not a crisis. But it’s not clarity, either, and Donna finds herself struggling with living in this place of uncertainty.
“I like to have a plan, and I like to know what we’re going to do. I’m finding it very hard for me to just wait and see.”
Still choosing more
Through her diagnosis, treatment, recurrence, and all the unexpected turns in between, Donna has held onto a simple mindset:
“I didn’t survive to be basic.”
It’s a phrase that stuck with her early on and has continued to shape how she moves through each new chapter. And for Donna, that means continuing to choose a full life, even in the unknown.
If you or someone you love has been diagnosed with lung cancer, know that you're not alone. Our HelpLine provides free, one-on-one support to people impacted by the disease. Call 1-800-298-2436 or email support@go2.org to connect. Our team is available Monday-Friday from 9 a.m.-5 p.m. ET/6 a.m.-2 p.m. PT.